


An ankylosing spondylitis flare-up is a period when symptoms such as back pain, stiffness and fatigue become worse than usual. Day-to-day self-care can support movement and comfort, but a new or persistent change also needs review with your rheumatology team. Use your agreed flare plan and keep taking medicines as prescribed unless your care team tells you otherwise.
Understanding ankylosing spondylitis
Ankylosing spondylitis, or AS, is a form of axial spondyloarthritis. It mainly affects the spine and the sacroiliac joints where the pelvis meets the spine. Other joints, the eyes and the bowel can also be involved. Symptoms often begin in early adulthood, but the condition can be recognized later and affects people of different sexes.
Genetics and other factors contribute. HLA-B27 is associated with AS, but having this marker does not mean you will develop the condition, and its absence does not rule it out. There is no single diagnostic test. A rheumatologist uses the history, examination, blood tests and imaging together. Johns Hopkins describes symptoms and assessment.
Common problems include lower back or buttock pain, morning stiffness, reduced movement and fatigue. Pain may disturb sleep and improve with movement. Over time, some people develop joint damage or spinal fusion. A painful week does not establish that fusion has occurred, and self-care alone cannot determine disease activity.
Ankylosing spondylitis is uncommon, affecting roughly 0.1% to 0.5% of the population. It is diagnosed more often in men than women, at a ratio of about 3:1, and it usually begins in the late teens or early twenties. Reported rates also vary between ethnic groups. These figures describe populations, not any individual prognosis.
What Is Inflammatory Back Pain?
Inflammation can cause back pain when the immune system mistakenly attacks joints in the spine. This is called inflammatory back pain. It is chronic back pain, lasting three months or more, that is felt deep in the buttocks or the low back. It is typically associated with ankylosing spondylitis but can also occur with other types of arthritis, and back pain due to inflammation can also follow an injury or an infection. Between 5% and 20% of people with chronic back pain have inflammatory back pain.
Signs of Inflammatory Back Pain
If your back feels inflamed, signs that point to inflammatory back pain rather than another type include:
- Back pain that has lasted three months or more and began before age 40
- A slow, gradual onset
- Morning pain and stiffness lasting more than 30 minutes
- Pain that eases with exercise, movement or a hot shower
- Pain that gets worse in the evening or with rest
- Tenderness in the sacroiliac (SI) joint, often felt as buttock pain that switches sides
Your primary care provider may refer you to a rheumatologist. Blood tests and imaging such as X-rays or MRI help show whether inflammation in the SI joint is behind the pain.
Inflammatory Back Pain Treatment
Treatment for inflammatory back pain usually combines movement and medicine, guided by your primary care provider or rheumatologist. Inflammatory back pain responds well to exercise, so a physiotherapist may suggest low impact exercise that avoids jarring the affected joints. Care providers often start with a nonsteroidal anti-inflammatory drug (NSAID), such as ibuprofen or naproxen, for relief of lower back pain and stiffness, and may try one for two to four weeks to see whether it works. If NSAIDs are not effective, they may prescribe biologic drugs such as TNF inhibitors, which reduce the inflammation causing the back pain.
There is no single best anti-inflammatory for lower back pain caused by AS. ASAS-EULAR guidance does not favor one NSAID over another, so the choice depends on your stomach, heart, and kidney health and on how well a medicine works for you. Common options include ibuprofen (Advil), naproxen (Aleve), and the prescription medicine celecoxib (Celebrex). A pharmacist or doctor can help you weigh the risks before you take one regularly.
Other Types of Back Pain
Inflammatory back pain is one major category. Other back pain falls into 4 types: mechanical, degenerative, oncologic and infectious. Mechanical back pain is the most common and comes from an injury to the spine, the discs, or nearby muscles or soft tissue. Degenerative back pain comes from bone loss due to osteoporosis or joint damage from osteoarthritis. Oncologic back pain comes from tumors that have spread to the spine, and infectious back pain comes from infections of the spine, discs, muscles or nearby soft tissue.
Recognizing a flare and knowing when to seek help
Compare symptoms with your usual pattern. Note where pain occurs, how long morning stiffness lasts and whether fatigue or sleep disruption is limiting normal activities. Symptoms can vary without an obvious trigger. Poor sleep, stress or a change in activity may accompany worse symptoms, but a diary cannot prove that one of them caused inflammation.
Tell your rheumatology team when a flare is unusually severe, lasts longer than your agreed plan allows, keeps recurring or affects daily function despite treatment. New pain after an injury, infection or a medication problem may need a different response from an ordinary flare. Do not assume that every symptom is AS.
Symptoms that need urgent assessment
- A painful red eye, sensitivity to light or blurred vision needs urgent eye assessment because AS can be associated with uveitis.
- New difficulty passing urine, loss of bladder or bowel control, numbness around the genitals or anus, or severe or worsening weakness or numbness in both legs needs emergency care.
- Seek urgent assessment for significant new neck or back pain after an injury. AS can increase the risk of spinal fractures. Severe chest pain or sudden difficulty breathing also needs urgent care.
The NHS complication guide explains uveitis, fracture risk and nerve compression warning signs. Fever or signs of infection should be discussed promptly, particularly if you take immune-suppressing treatment. Follow the infection advice supplied with your medicine.
A practical self-care plan during a flare
Use a balance of manageable movement and short rests. Reduce the intensity or duration of an activity that aggravates symptoms rather than forcing through severe pain. Ask your physiotherapist which gentle exercises to continue on worse days. Long periods of inactivity can increase stiffness.
Warm showers or a wrapped heat pack may ease muscle tightness. Some people prefer a wrapped cold pack for a painful area. Protect your skin and stop if either makes symptoms worse. Avoid sleeping on a heating pad. Comfort measures do not replace treatment for active inflammation.
Plan essential tasks for the part of the day when you function best. Split demanding chores into shorter sessions and ask for practical help when needed. Keep a clear plan for whom to contact, when to call and what changes your clinician has already authorized.
Exercise and physiotherapy between flares
Regular movement is part of AS care. A physiotherapist can tailor stretching, strengthening, posture and breathing exercises to your mobility and disease activity. Water-based exercise can make movement easier. The NHS treatment guide describes physiotherapy alongside medicines.
- Walking, swimming or water aerobics can provide aerobic activity. Cycling may suit some people if the position is comfortable and safe.
- Gentle stretching and modified yoga can work on mobility. Ask for adapted positions rather than forcing a twist or stretch.
- Resistance bands or light weights can support strength when a physiotherapist has shown you appropriate form.
- Begin gently, warm up and build activity gradually. Supportive footwear and a safe setup matter. Stop and seek advice for new or sharp pain.
Exercise choice needs particular care if you have spinal fusion, osteoporosis or a previous fracture. Ask before starting contact sports, high-impact activity or forceful spinal movements. There is no single routine that is safe for every person with AS.
Posture, sleep and fatigue
Change position during the day and arrange your desk and daily tasks to reduce uncomfortable bending. Follow posture exercises recommended by your physiotherapist. Do not force your back flat or adopt a painful sleeping position to match generic posture advice.
Keep a regular sleep routine, limit late caffeine and allow time to wind down. If pain repeatedly wakes you, discuss treatment and sleep positioning with your team. Persistent fatigue can have more than one cause and deserves review. The Arthritis Foundation self-care guide covers movement, posture, sleep and stopping smoking. Smoking can worsen AS outcomes. Ask for help quitting if needed.
Food choices and diet claims
No diet has been established as a cure for AS. A varied diet with vegetables, fruit, whole grains, protein foods and unsaturated fats supports general health. Fish, olive oil, nuts or other foods can fit that pattern according to your preferences and needs. A dietitian can help if bowel disease, weight loss, poor appetite or restrictions complicate eating.
Do not assume that dairy, gluten, red meat or carbohydrates trigger a flare for everyone. Some people notice a pattern, but one episode after a meal does not prove cause. If you want to try a dietary change, record symptoms and review it with your clinician or dietitian so the diet remains adequate. Supplements and restrictive diets can also have costs and risks. The Spondylitis Association of America cautions against cure-all diet claims.
How medical treatment and self-care fit together
Self-care supports comfort, mobility and coping. It does not replace medicines needed to control inflammation. Nonsteroidal anti-inflammatory drugs may help pain and stiffness when suitable. Persistent disease activity can lead a rheumatologist to consider targeted treatments, including biologic or JAK-inhibitor medicines. Choice depends on your health history and other conditions.
Conventional DMARDs such as sulfasalazine or methotrexate may be used for joints outside the spine. They are not established treatment for spinal symptoms. Steroid injections sometimes have a role for a particular inflamed joint. Do not start steroids, increase pain medicines or reduce treatment because self-care seems to be helping without following your clinician's plan.
Keep scheduled reviews and required monitoring. Ask what to do with a missed dose, side effects or an infection. Severe joint damage occasionally requires surgery, but most people with AS do not need it. Treatment choices and follow-up are outlined in the NHS AS treatment guidance.
Mental health and support
Pain, fatigue and uncertainty can affect mood, relationships and independence. Explain the practical help you need to people you trust. An AS or axial spondyloarthritis support group can offer shared experience, while a mental health professional can help with persistent anxiety, low mood or difficulty coping.
Try a short relaxation practice if it is comfortable: slow breathing, a guided meditation or gentle release of tense muscles. Adapt movement-based activities such as yoga or tai chi with professional advice. These practices can support coping. They do not establish that symptoms are psychological or replace assessment of worsening pain.
Common Questions About Arthritis Flare-Ups
Arthritis is not a single disease. It is a group of conditions that cause joint pain, stiffness or swelling, including AS, rheumatoid arthritis (RA), psoriatic arthritis (PsA) and osteoarthritis (OA). Any of them can flare, and some causes and symptoms are shared while treatment often depends on the type.
RA, PsA and AS are forms of inflammatory arthritis, in which the immune system causes the joint inflammation. Reactive arthritis is another inflammatory type that develops after an infection, often of the bowel or genitals. A later infection can cause it to flare up again, so mention any recent infection when you report new flare-ups.
What are the symptoms of arthritis?
The symptoms of arthritis vary depending on the type of arthritis. RA and PsA can cause joint pain, stiffness, swelling, and loss of range of motion. OA typically causes pain and stiffness in the joints that are affected. Arthritis can also cause the formation of bone spurs, which are small outgrowths of bone. Bone spurs can press on nerves and cause pain.
What causes arthritis flare-ups?
An arthritis flare can be gradual or sudden. There is no single reason for it, because there are many different types of arthritis, and each type can have different triggers. Some possible triggers that can make arthritis flare up include:
- Infections can trigger flare ups because they cause inflammation in the body. This can be a particular problem for people with rheumatoid arthritis, as they are more susceptible to infections.
- Stress because of an illness or injury can cause the immune system to go into overdrive, which can lead to a flare-up of rheumatoid arthritis.
- Hormonal changes play a role because some types of arthritis, such as rheumatoid arthritis, are more common in women than men. This may be due to the fact that hormones can affect the immune system.
- Weather affects arthritis because barometric pressure changes can cause swelling and pain in the joints and muscles. Cold weather can make the pain and stiffness of arthritis worse, while warm weather can provide some relief.
What is the weather and arthritis index?
The weather and arthritis index is a tool that can help you predict when arthritis flare-ups may occur. The index uses a combination of barometric pressure, temperature, and humidity to generate a forecast for the next two days.
If the index is high, it means that the conditions are favorable for a flare-up. If the index is low, it means that the conditions are not as favorable for a flare-up. However, it is important to remember that the weather and arthritis index is just a tool, and that other factors can also cause arthritis flare-ups.
Other factors include:
- Injury or trauma
- Excess weight
- Certain medications
How can I manage my arthritis flare-ups?
If you suffer from regular arthritis flare-ups, it is important to work with your doctor to develop a management plan. This may involve lifestyle changes, such as losing weight or avoiding certain triggers, as well as medication. Some medications that are used to treat and control arthritis flare-ups include: Nonsteroidal anti-inflammatory drugs (NSAIDs), Corticosteroids and Disease-modifying antirheumatic drugs (DMARDs).
To help stop an arthritis flare-up from getting worse, it is important to rest and avoid any activities that may aggravate your symptoms. You should also apply ice to the affected joint for 20 minutes at a time, several times a day. If your symptoms are severe, you should contact your doctor. They may prescribe additional medication or recommend other treatments, such as physical therapy.
Arthritis flare-ups can be painful and disruptive, but there are things you can do to manage them. Work with your doctor to develop a plan that works for you, and be sure to rest and apply ice to the affected joint when a flare-up occurs.[4][5]
What are some tips for managing arthritis flares?
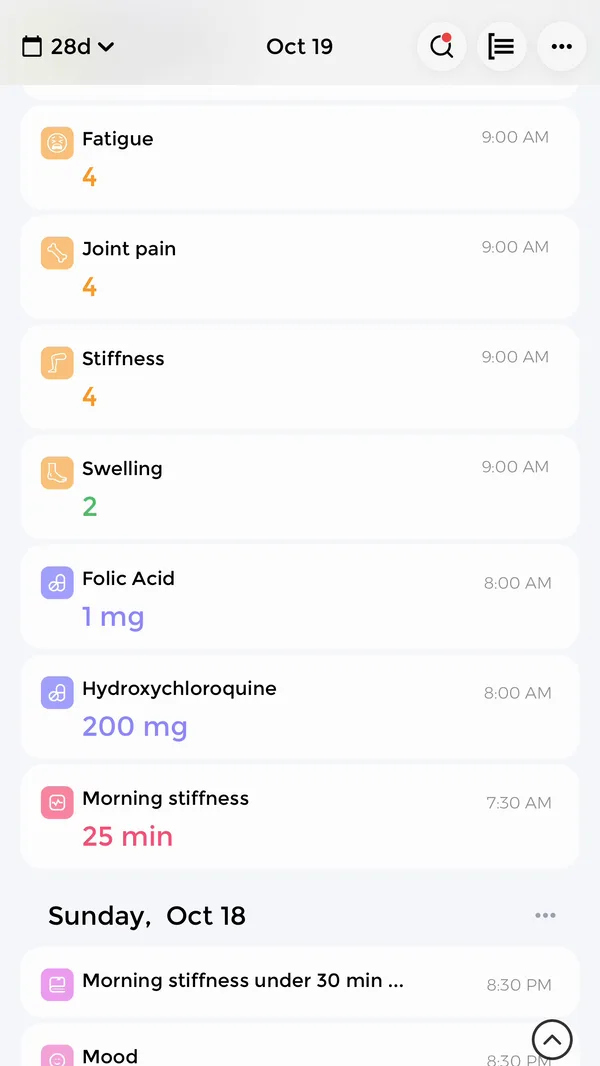 There are many things you can do to manage your arthritis flares, including:
- Resting: When you are experiencing a flare, it is important to rest the affected joint. This will help reduce inflammation and pain.
- Applying ice: Applying ice to the affected joint for 20 minutes at a time can help reduce swelling and pain.
- Taking medication: If your primary care doctor has prescribed medication for your arthritis, such as:
- Nonsteroidal anti-inflammatory drugs (NSAIDs): These medications can help reduce chronic pain and inflammation. Examples of NSAIDs include ibuprofen and naproxen.
- Corticosteroids: These medications can help reduce inflammation. Examples of corticosteroids include prednisone and methylprednisolone.
- Disease-modifying antirheumatic drugs (DMARDs): These medications can help slow the progression of arthritis. Examples of DMARDs include methotrexate and hydroxychloroquine.
- Avoiding triggers: If you know what triggers your arthritis flares, try to avoid them. This may require making some lifestyle changes, such as losing weight or changing your diet.
- Managing stress: Stress can trigger arthritis flares, so it is important to find ways to manage stress. This may involve yoga, meditation, or other relaxation techniques.
Arthritis flares can be painful and disruptive, but there are things you can do to manage them. Work with your nurse practitioner to develop a plan that works for you, and be sure to rest and apply ice to the affected joint when a flare-up occurs.[6]
What is an Arthritis flare up?
A flare up can be very painful and uncomfortable. It is a time when the symptoms of the disease become worse, and can last for a few days or several weeks. For some people with arthritis, flare-ups are a regular occurrence, while others only have a few per year. Regardless of how often they happen, flare-ups should always be taken seriously, as they can be quite painful and debilitating.[1][2][3]
What does a flare feel like?
The symptoms of a flare can vary depending on the type of arthritis you have. However, some common symptoms include:
- Joint pain and stiffness
- Swelling in the joints
- Redness and warmth in the joints
- Fatigue
- Weakness
- Fever
- Weight loss
For people with rheumatoid arthritis, flare-ups can also cause skin rashes and mouth sores.
How long does an arthritis flare up last?
Based on patient surveys, we know that the majority of arthritis flare-ups last between 3 and 14 days. However, some flares can last longer, especially if they are not treated properly. They last this long because they require time for the immune system to calm down and for the inflammation to resolve.
What is the difference between a flare and remission?
A flare is when the symptoms of arthritis become worse. This can be due to many different factors, such as infection, stress, or weather changes. Remission is when the symptoms of arthritis improve. This may be due to medication or lifestyle changes.
Rheumatoid Arthritis Flare-Ups
RA is an autoimmune condition in which the immune system attacks the lining of the joints. A flare, also called an exacerbation, is a period when this inflammation becomes more active. Many people with RA have flares from time to time, even when the condition is generally well controlled.
What Does a Rheumatoid Arthritis Flare-Up Feel Like?
During an RA flare, inflammatory symptoms tend to appear in the same joints on both sides of the body, and morning stiffness often lasts longer than usual. A larger joint such as a knee can flare as well as the small joints of the hands, wrists and feet. The signs often build over a day or two as inflammation increases, although some flares come on quickly.
What Triggers Rheumatoid Arthritis Flare-Ups?
Infection and stress are two of the best-known causes of RA flares. Poor sleep, overdoing activity and missed or reduced doses of medicine can also bring one on, and smoking makes RA worse over time. Some flares have no clear cause at all. If your joints keep flaring up or your arthritis seems to be getting worse, it is a sign to review your treatment with your rheumatology team.
How Long Does a Rheumatoid Arthritis Flare-Up Last?
RA flare-ups vary in length from person to person and from one flare to the next. A mild flare may settle within days on your usual plan, while a more severe one can last for weeks until treatment brings the inflammation under control. The duration and pattern of your flares help your rheumatology team judge whether treatment is working, so mention longer or more frequent flares at your next contact.
How Is a Rheumatoid Arthritis Flare-Up Treated?
Contact your rheumatology team early in an RA flare-up so treatment can start promptly. During a bad flare, they may suggest a short course of steroid tablets, a steroid injection into a swollen joint or a change to your regular medicine. Keep taking your usual treatment unless they tell you otherwise.
Can You Have Flare-Ups with Osteoarthritis?
Yes. Like other types of arthritis, OA can flare. It develops when the cartilage that cushions the ends of the bones gradually breaks down. During an OA flare, symptoms include sharper joint pain, stiffness and sometimes swelling in a joint that already has osteoarthritis, most often a knee, hip or hand. How long an osteoarthritis flare-up lasts varies, but most settle over a few days or weeks as the acute pain eases.
What Causes Osteoarthritis Flare-Ups?
The most common trigger is asking more of a joint than it is used to, such as a long walk, heavy lifting, gardening or a new exercise. A knock, twist or fall can also cause a sudden flare-up of joint pain, and extra body weight makes the knees and hips work harder. Sometimes no clear cause is found.
Treatment for an osteoarthritis flare-up usually means easing back on the activity that set it off without stopping movement altogether and taking a pain reliever your doctor or pharmacist recommends. Once it settles, regular exercise and strengthening help protect the joint.
Arthritis Medicines and Outlook
What Is the Most Effective Medication for Arthritis?
No single medicine works best for everyone, because the right choice depends on the type of arthritis, the joints involved and your other health conditions. For osteoarthritis pain, an anti-inflammatory gel or cream rubbed into a sore knee or hand is often tried first, and anti-inflammatory tablets such as ibuprofen or naproxen are sold over the counter. These are not safe for everyone, so ask a pharmacist to help you choose the best OTC medication or cream for your arthritis.
For inflammatory types such as RA, PsA and AS, the most effective treatment is usually a prescription plan from a rheumatologist that controls the inflammation itself. Celecoxib (Celebrex) is a prescription anti-inflammatory whose uses include osteoarthritis, rheumatoid arthritis and ankylosing spondylitis.
Can Rheumatoid Arthritis Be Cured Permanently?
There is no permanent cure for RA yet, but it can often be controlled well. Starting treatment early and taking it consistently gives the best chance of remission. No home remedy, diet or supplement can cure arthritis permanently. Staying active, not smoking and keeping a healthy weight still support your treatment and how you feel day to day.
Keeping a useful AS record
Record pain location and severity, morning stiffness, fatigue, sleep, activity and medication use. Include new eye or bowel symptoms and how daily tasks are affected. A simple record is enough to help compare changes over time and prepare for your next appointment.
You can use a notebook or the CareClinic self-care journal to organize entries and medication reminders. Bring the record to your care team. An apparent trigger in a log is a question to explore, not proof, and tracking should never delay urgent care.
References
- "Osteoarthritis Flares - PMC". https://www.ncbi.nlm.nih.gov/pmc/articles/PMC10523485/
- "How Long Does a Flare Last?". https://www.arthritis.org/diseases/more-about/how-long-does-a-flare-last
- "Tips to Cope with Arthritis Flares | Arthritis Foundation". https://www.arthritis.org/health-wellness/healthy-living/managing-pain/pain-relief-solutions/coping-with-an-arthritis-flare
- "How to maintain movement during a flare up | Versus Arthritis". https://www.versusarthritis.org/news/2025/january/how-to-maintain-movement-during-a-flare-up/
- "Managing a flare - Rheumatology". https://www.ouh.nhs.uk/rheumatology/information/patients/advice/flare/
- "Coping With Pain: Relaxation and Stress Reduction Techniques for Living with Arthritis". https://www.arthritis.org.au/arthritis/arthritis-insights/positive-health-habits/coping-with-pain-relaxation-and-stress-reduction-techniques-for-living-with-arthritis/